Saved
Robotics · Systems

Da Vinci Surgical System

A costly, team-dependent robot that extends laparoscopy — not replaces it — and has never proved better than the scalpel it was meant to upgrade.

Worth your time?3/5No.The brief is enough.What works, what does not, who it is for ↓
10:58in productionCh. 1 · Not a robot surgeon/ 10:58 · ceiling 15 min
6 chapters · 10:58Ceiling 15:00

The brief is written and checked. The video joins this page when it is cut.6 chapters · 1 min read · 10:58 planned

Read the brief

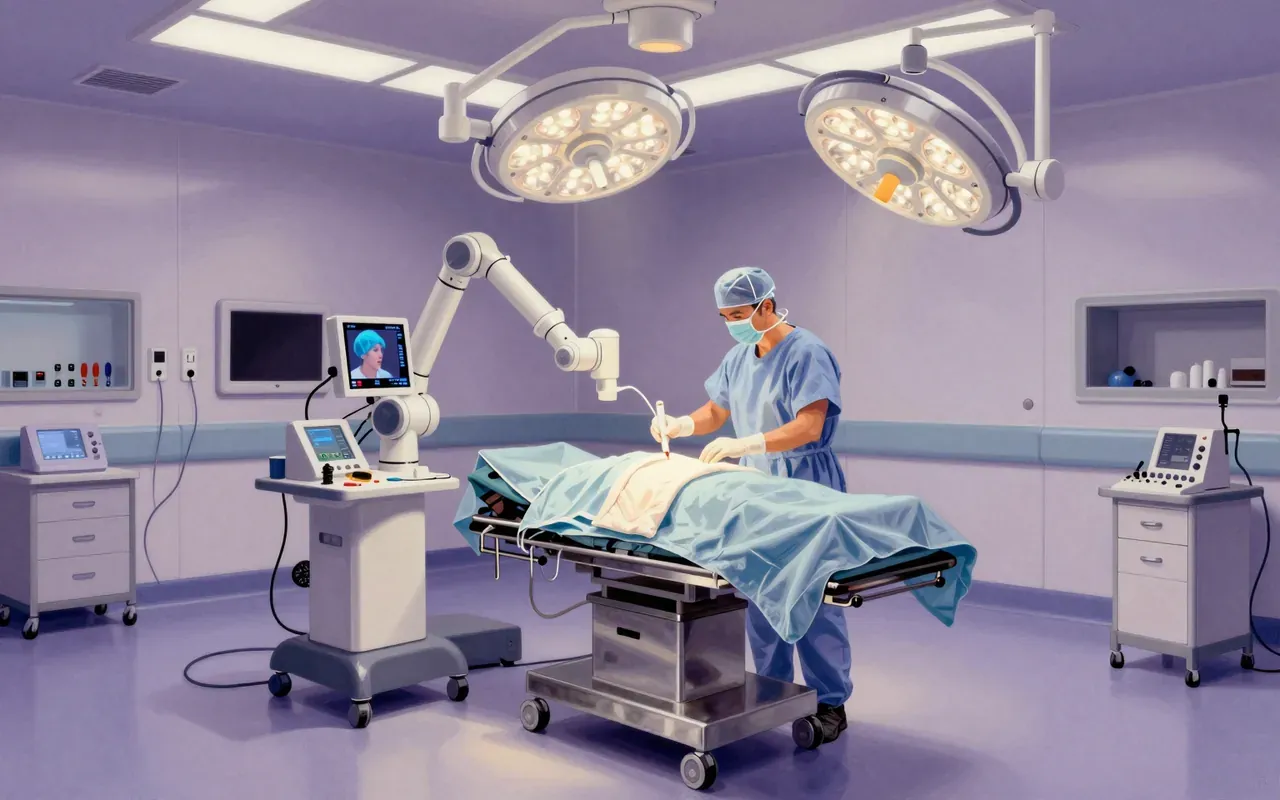
The Da Vinci Surgical System is a teleoperated robotic platform for minimally invasive surgery. It translates surgeon hand motions at a console into precise movements of up to four robotic arms at the patient’s side — one for 3D vision, the rest for tools. FDA-cleared in 2000, it had performed ~200,000 surgeries by 2012, mainly prostatectomies and hysterectomies. It does not demonstrate long-term superiority over laparoscopy. It demands high capital cost, proprietary software, dedicated training, and a full surgical team. Safety investigations by the FDA include reports of patient injury and death.

Chapters & takeaways6
  1. 0:57
    Not a robot surgeon

    It is a surgeon-controlled robotic platform for minimally invasive surgery — not autonomous, not AI-driven.

  2. 2:13
    Two boxes, four arms

    It requires two physical components: a surgeon’s console and a patient-side cart with 3–4 arms — one for vision, the rest for tools.

  3. 3:11
    Prostate first, then everything else

    By 2012, it had performed ~200,000 surgeries — mostly prostatectomies and hysterectomies — with later expansions into cardiac and gynaecologic use.

  4. 4:23
    Cleared before proven

    FDA clearance came in 2000; prostate-specific approval followed in 2001. Marketing began in Europe in 1999.

  5. 5:33
    Named for anatomy, not automation

    Its name honours Leonardo da Vinci’s anatomical studies — which led to the first known robot design — not his engineering prowess.

  6. 7:10
    Minimally invasive ≠ minimally consequential

    It delivers a minimally invasive approach, but no verified evidence shows improved long-term outcomes versus laparoscopy.

3 more chaptersFewer chapters
Worth your time?

No. The brief is enough.

3/ 5
What works
  • enables complex soft-tissue resection through small incisions
  • delivers magnified 3D visualisation
  • provides wristed instrument articulation beyond human hand range
  • supports expansion into thoracoscopic and cardiac valve procedures
What does not
  • prove long-term superiority over laparoscopy
  • eliminate need for surgical team
  • resolve proprietary software constraints
  • close FDA safety concerns
Study it if
  • hospital procurement leads with budget for high-volume urology/gynaecology units
  • surgeons trained and credentialed on the system
  • institutions able to absorb service contract costs
Skip it if
  • clinicians seeking evidence-based outcome improvement
  • health systems prioritising cost-per-procedure efficiency
  • teams without dedicated robotics support staff
Who should study it, and who should skipHide who it is for
The written brief1 min read

What it is and the problem it solves

It is a robotic, minimally invasive surgical platform. It solves the problem of limited dexterity and visual fidelity in standard laparoscopy by translating hand movements into precise, scaled, tremor-filtered motions inside the body.

How it works

The surgeon sits at a console and manipulates controls to move three or four robotic arms on a patient-side cart. One arm holds 3D cameras. The others hold surgical tools: scalpels, scissors, electrocautery devices, or graspers. A surgical team must be present to operate the system and ensure patient safety.

What works

It enables surgeons to perform complex soft-tissue procedures — especially prostatectomies and hysterectomies — through small incisions with enhanced 3D vision and articulating instruments. By 2012, it had been used in ~200,000 surgeries.

What does not

It does not establish long-term clinical superiority over conventional laparoscopy. It does not eliminate the need for a full surgical team. It does not overcome proprietary software limitations or resolve FDA safety concerns tied to patient injuries and deaths.

What it changes

It changes surgical workflow by inserting a remote-controlled robotic interface between surgeon and tissue. It shifts capital expenditure toward proprietary hardware and recurring service contracts. It expands the scope of minimally invasive procedures to cardiac valve repair and thoracoscopic surgery — but only with adjunctive incisions.

Is it worth your time

It is worth your time only if you manage procurement for high-volume urology or gynaecology units and can absorb its cost, training burden, and proprietary lock-in — not if you seek proven clinical superiority over laparoscopy.
Same field · Robotics4 of 29
8:49
Humanoid robotHumanoid robots are anthropomorphic test platforms—defined by torso, head, two arms, two legs—not autonomous agents. They enable prosthetic and orthotic development through biomechanical fidelity, not AI. WABIAN-2 is used in lower-limb rehab. Knowledge transfer to clinical devices is documented. They do not operate autonomously or replace human care. Their value is narrow, mechanical, and experimental.
9:51
ExoskeletonsHuman exoskeletons are wearable mechanical devices that apply force to the body to assist motion, posture, or activity. Powered versions use electric motors; passive ones use springs or elastic materials. ReWalk achieved FDA approval in 2014—the first such device—enabling supervised upright gait for paralysed users. But full-body, untethered, real-world use remains limited. They shift rehabilitation and occupational ergonomics—but not mobility independence.
12:34
ASIMOHondaASIMO was Honda’s eleventh humanoid robot, built to test bipedal navigation in human environments. It worked — but only in narrow conditions. It climbed stairs autonomously, yet fell twice. It recognised faces and gestures, but only pre-trained ones. It ran one hour on lithium-ion power, but never left the lab. Retired in 2022, it changed robotics research, not robotics use.
10:28
Intuitive Surgical1995Intuitive Surgical did not invent robotic surgery. It licensed SRI’s late-1980s research, incorporated in 1995, refined the system into 'Lenny', tested it in 1997, launched in Europe in 1999, and secured staggered FDA approvals from 2000 onward. It delivers telemanipulated, minimally invasive surgery—but only where approved, only with a surgeon present, and only as hardware, not intelligence.
Up next in Technology

Internet protocol suite

Vint Cerf and Bob Kahn · 1975 · 9:03

TCP/IP did not invent the internet—it outsourced reliability to every machine that joined it.

9:03